

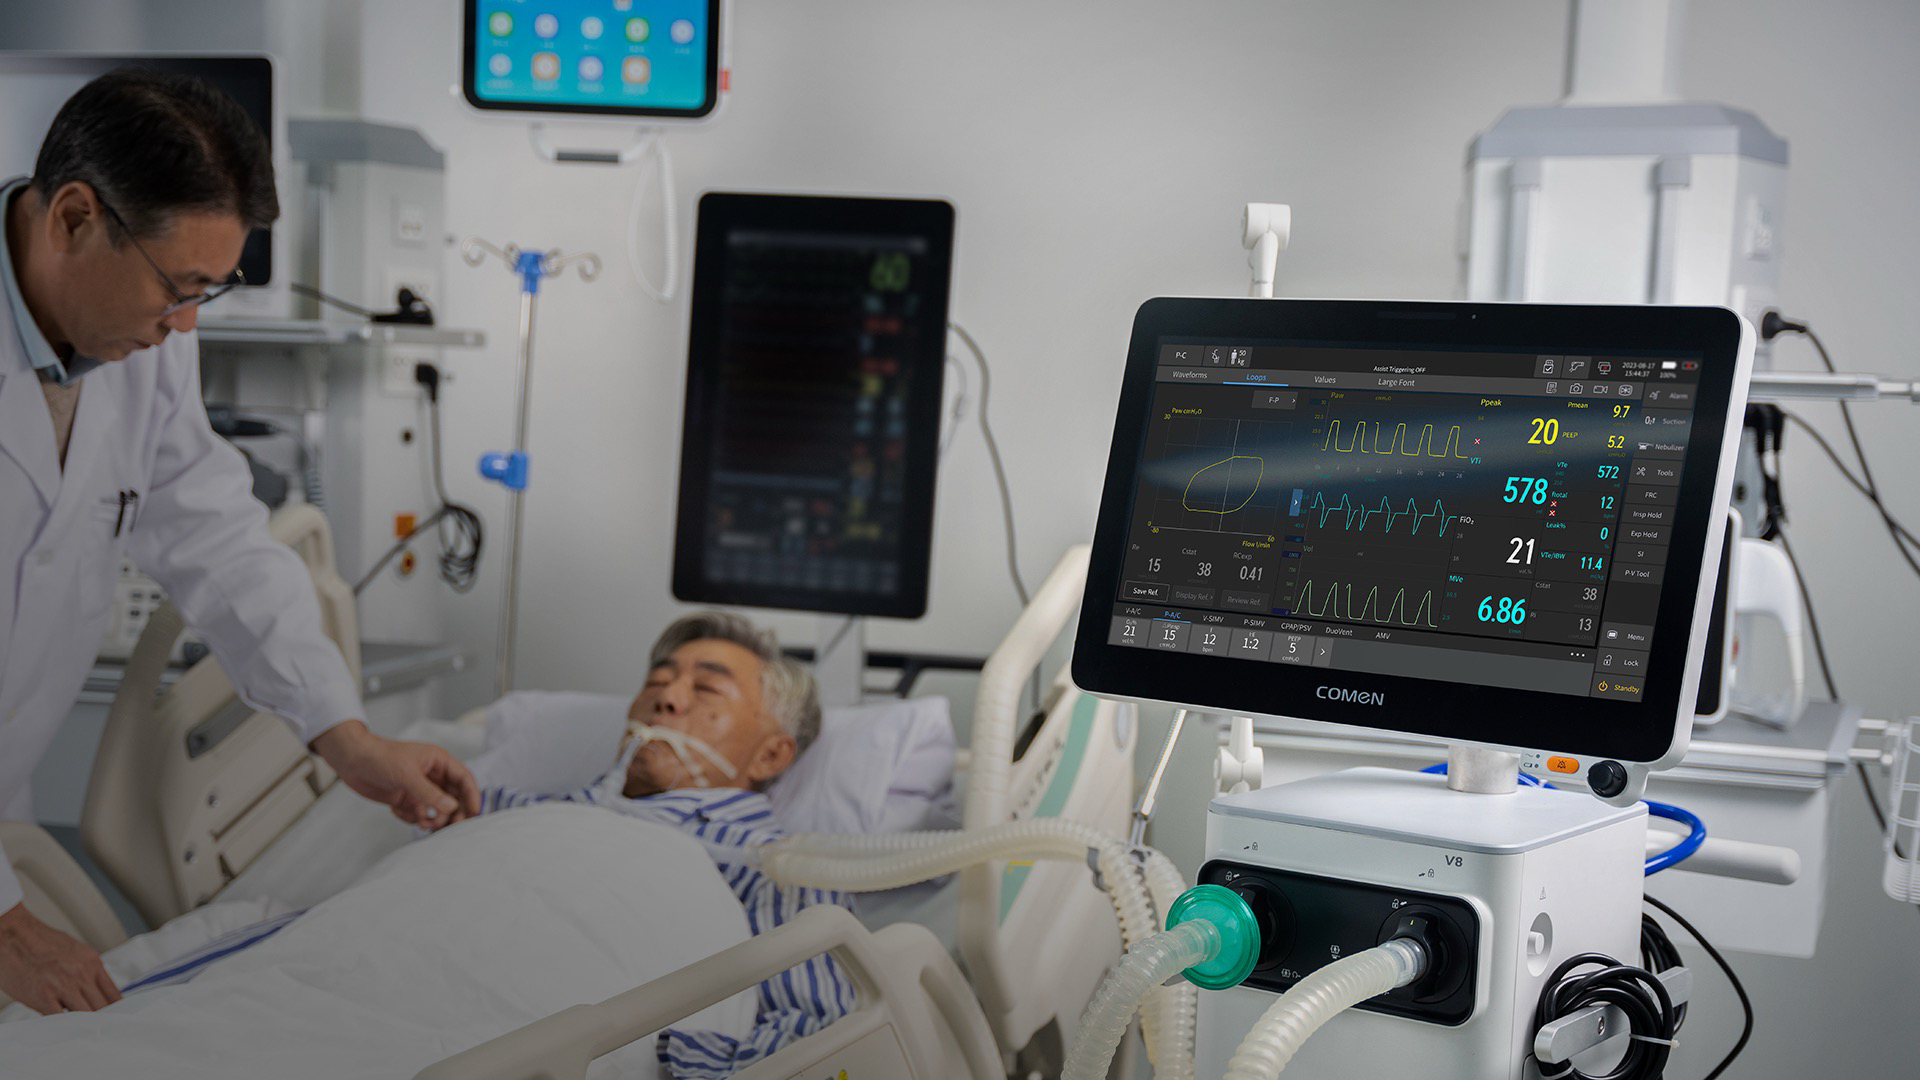
When the tools tell a story
I remember a night in March 2018 at St James’s Hospital (Dublin): a single infusion pump kept tripping an alarm, 42 failed cycles in three days — and we all asked the same blunt question: why are machines built like this? That hospital incident pushed me to write about the way a medical equipment brand can either soothe or stir clinical frustration — and what sits beneath the surface of common fixes. As a medical equipment manufacturer, I have watched design choices that seemed sensible on paper become service headaches on the ward; the small things — an awkward connector, unclear error codes — add up. Sure, there’s craic and comfort in an old way of doing things, but it’s the fault-lines I want to map. Let’s move to the nuts and bolts.
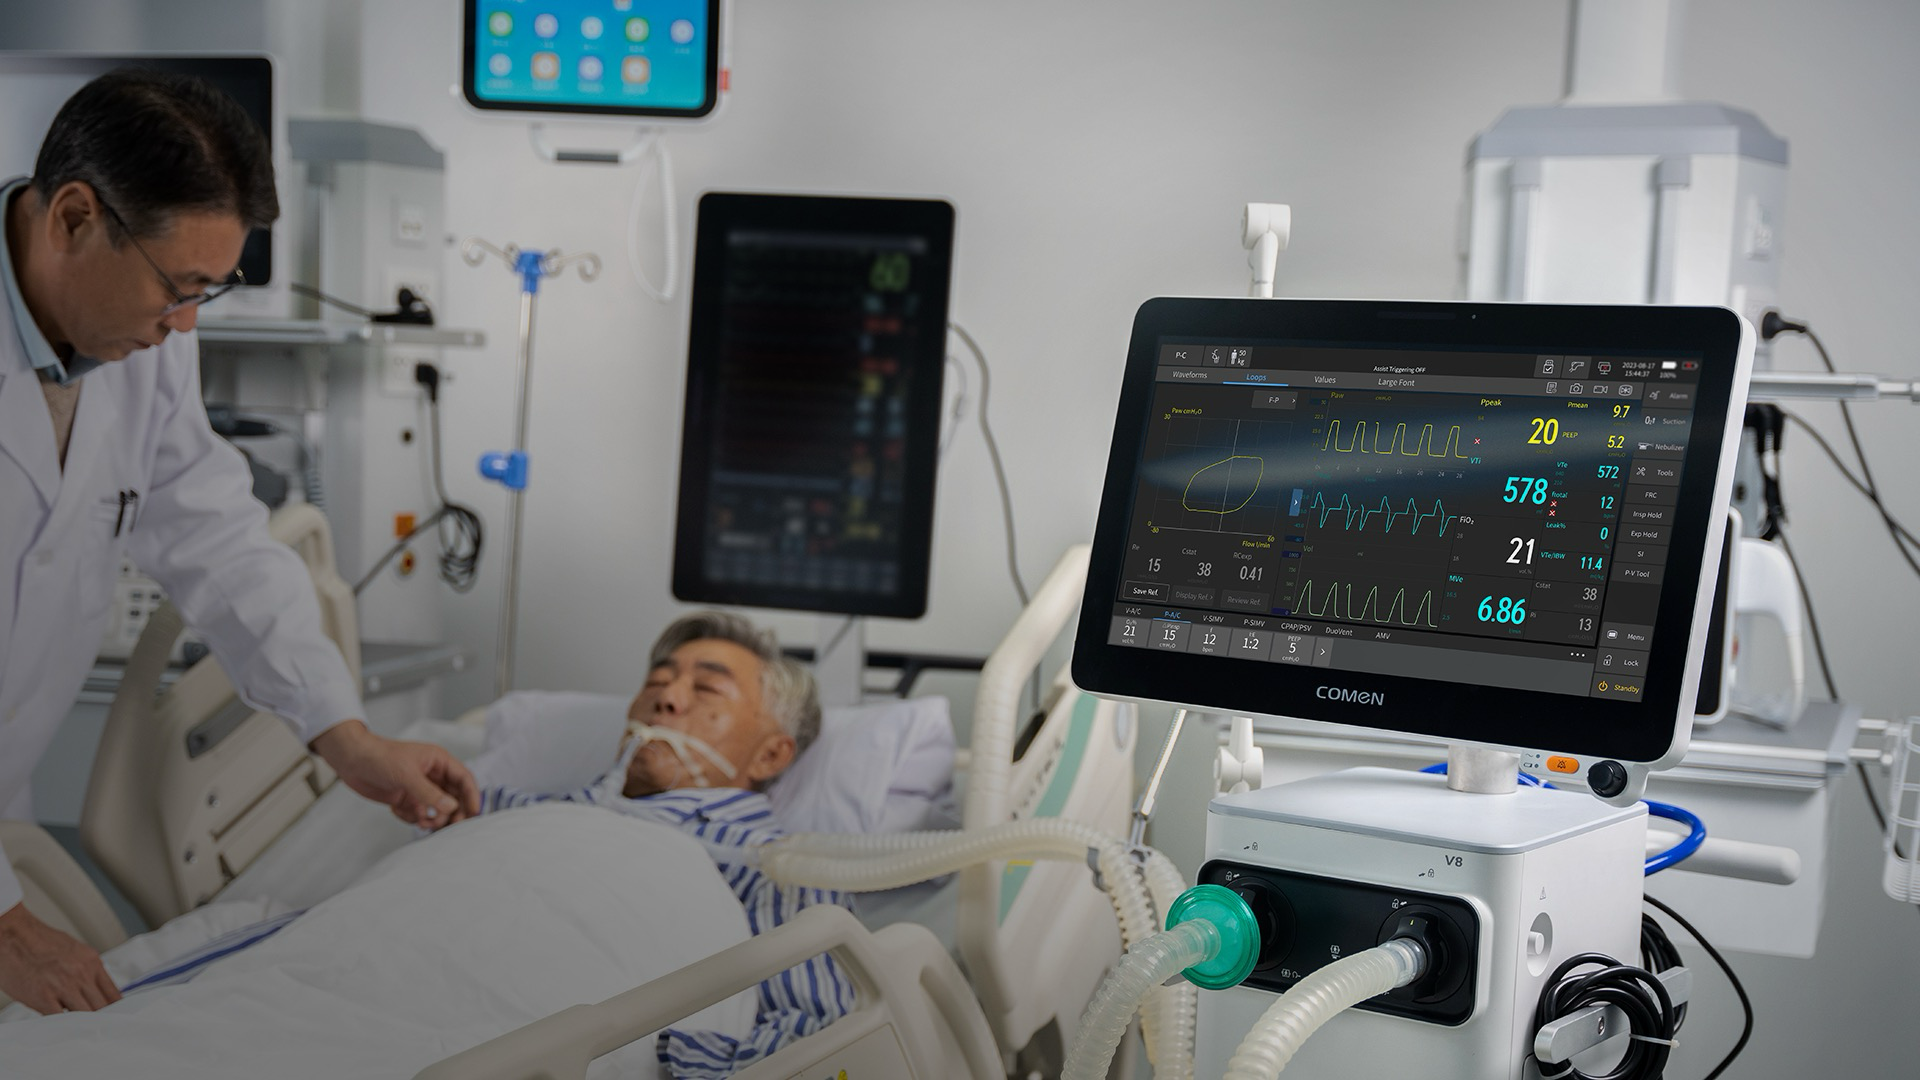
What’s the hidden flaw?
I’ll be frank: many traditional solutions rely on bolt-on patches rather than surgical redesign. In one retrofit project I led in Dublin in 2019, we replaced an ageing sterilizer controller and cut mean-time-to-repair by 27% — quantifiable, not hypothetical. The real flaw is not a single component; it’s the procurement and service chain. Poorly specified OEM parts, inconsistent calibration, and opaque regulatory paperwork leave hospital engineers juggling spare parts and service calls. I’ve stood beside a biomedical engineer at 02:30, swapping a power module on a ventilator because the supplier’s lead-time was six weeks — that is not acceptable. Those are the days when you feel the cost of bad design as downtime, as diverted staff time, as risk. I use terms like calibration, infusion pump, and sterilizer because they tie the conversation to real gear, not airy theory. We need to stop treating fixes as permanent solutions — they are temporary, costly, and they erode trust.
Now: tilt toward what will actually work
Here’s a blunt claim: modularity and remote diagnostics will separate the makers who help clinicians from those who merely sell boxes. I say this after overseeing two pilot lines where we introduced board-level modular swaps and secure telemetry — both cut on-site visits in half within six months. When a medical equipment brand builds for easy replacement and clear error telemetry, procurement teams save money and wards get uptime. We should measure things that matter: time-to-repair, spare-part footprint, and real-world service load. Regulatory compliance still matters — don’t skimp — but smarter design reduces the paperwork pile (and the headaches). Wait — there’s more nuance: predictive analytics are only useful if the data pipeline is reliable.
What’s next for buyers?
I want wholesale buyers to insist on three practical metrics when choosing suppliers: mean time to repair (MTTR) under local service conditions; percentage of field-replaceable modules versus vendor-only repairs; and documented reduction in service calls after deployment (aim for a measurable drop, e.g., 20–30% within a year). I’ve seen procurement win when teams demand test data from March deployments and when they visit a live ward to watch devices in use. Honest— that kind of on-the-floor scrutiny separates persuasive brochures from trustworthy partners. Compare manufacturers by those metrics, and the numbers will speak. Choose vendors who design for easy calibration, who provide clear error codes, and who back that with local spare stocks. No fluff. No jargon. Just results.

I’ve spent more than 15 years in B2B supply work — that hands-on time in hospitals, in workshops, at midnight swaps — taught me this: good design pays back in fewer alarms, less paper, and calmer staff. So, when you next evaluate a partner, ask for real field figures, demand modular spare strategies, and prefer the brand that shows you data from a real ward. The future is practical, and it starts with the right questions — COMEN.

